Sac-TMT and sonesitatug vedotin hit Phase 3 gastric survival while missing central PFS
Merck and Kelun-Biotech's (HKEX: 06990) TROP2 ADC sac-TMT (TroFuse-015, NCT06356311) and AstraZeneca/Keymed's (02162.HK) CLDN18.2 ADC sonesitatug vedotin (NCT06346392) both hit Phase 3 OS while missing BICR-PFS.
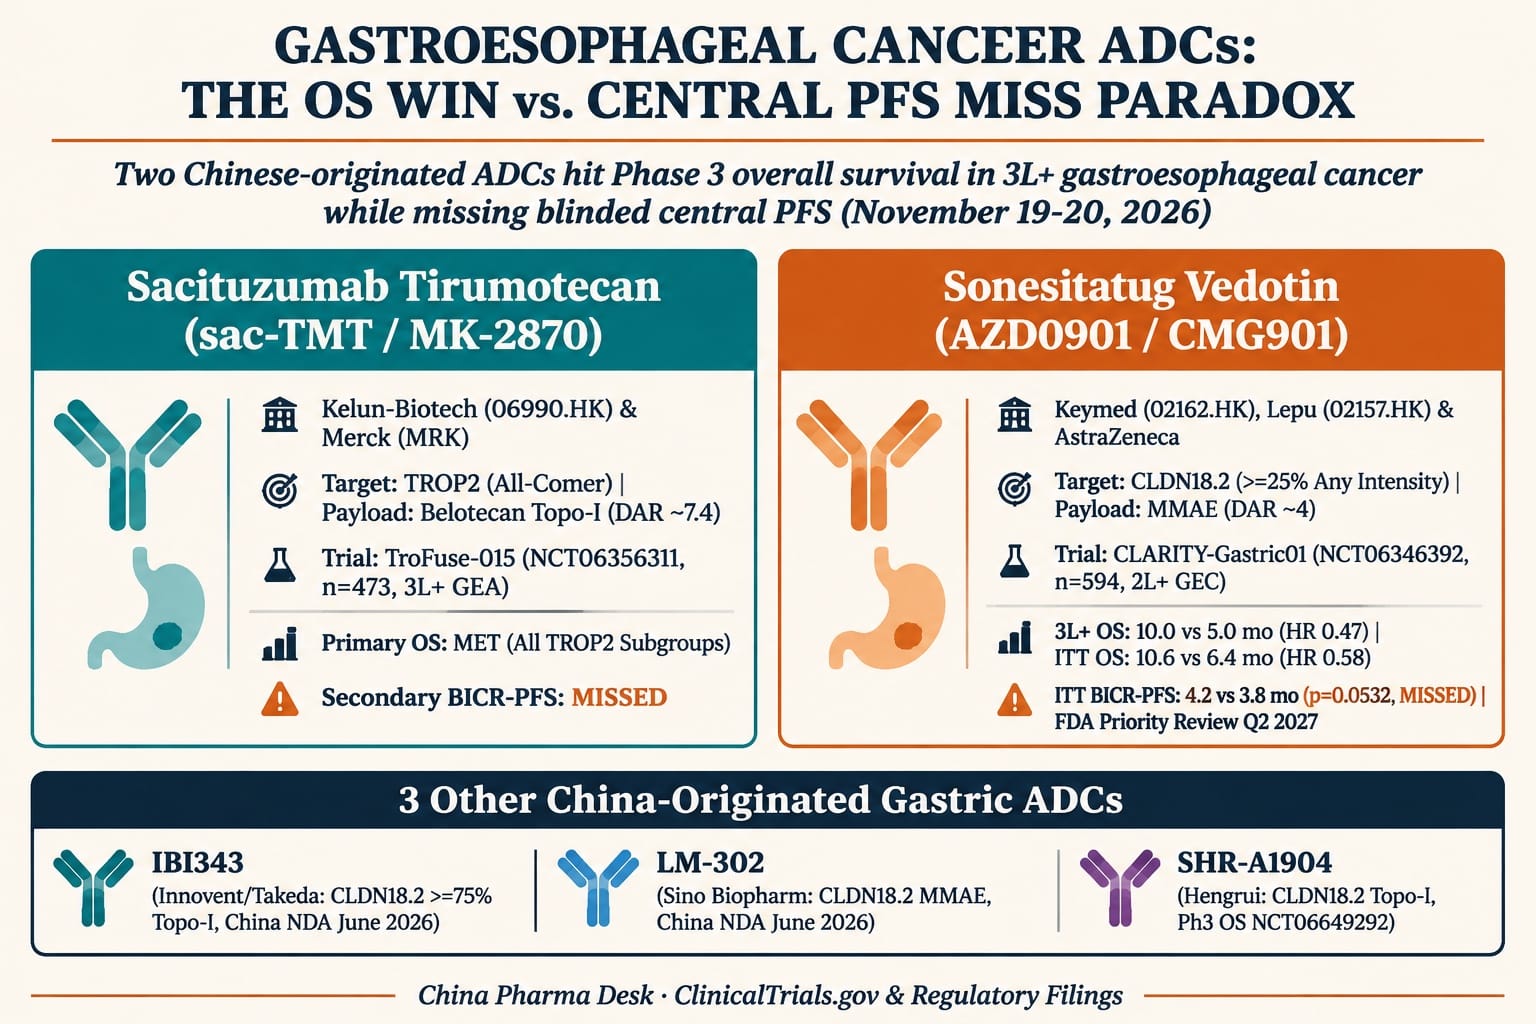
Within 24 hours on November 19 and November 20, 2026, two Chinese-originated antibody-drug conjugates (ADCs) advanced at the top of the global late-line gastroesophageal cancer landscape—and exposed the exact same statistical split between overall survival (OS) and blinded central progression-free survival (BICR-PFS). On November 20, Merck (NYSE: MRK) and Sichuan Kelun-Biotech Biopharmaceutical (HKEX: 06990) announced that the global Phase 3 TroFuse-015 trial (NCT06356311, n=473) of TROP2-directed ADC sacituzumab tirumotecan (sac-TMT / MK-2870 / SKB264) met its primary endpoint of OS in third-line or later (3L+) locally advanced unresectable or metastatic gastroesophageal adenocarcinoma (GEA), while missing its secondary endpoint of BICR-PFS. One day earlier, AstraZeneca (LSE/NASDAQ: AZN) and originators Keymed Biosciences (HKEX: 02162) and Lepu Biopharma (HKEX: 02157) disclosed that the U.S. Food and Drug Administration (FDA) accepted and granted Priority Review (target PDUFA action date in Q2 2027) to the Biologics License Application (BLA) for Claudin 18.2 (CLDN18.2)-directed ADC sonesitatug vedotin (Sone-Ve / AZD0901 / CMG901) based on the global Phase 3 CLARITY-Gastric01 trial (NCT06346392, n=594)—a study that doubled 3L+ median OS from 5.0 to 10.0 months (HR 0.47, p<0.000001) and improved intention-to-treat (ITT) 2L+ OS to 10.6 versus 6.4 months (HR 0.58, p=0.000004), yet narrowly missed its co-primary ITT BICR-PFS endpoint (4.2 versus 3.8 months, HR 0.77, p=0.053193).
For global oncology investors and regulatory teams, the twin announcements carry two immediate implications. First, five Chinese-originated ADCs—spanning TROP2, CLDN18.2, and EGFR×HER3—now anchor the late-stage global and domestic registration pipeline for pretreated gastric and gastroesophageal junction (GEJ) cancer. Second, in direct contrast to Akeso (HKEX: 09926) and Summit Therapeutics’ (NASDAQ: SMMT) ivonescimab FDA Complete Response Letter two weeks ago—where a PFS benefit without statistically significant OS failed U.S. review—the FDA’s grant of Priority Review to sonesitatug vedotin confirms that robust OS separation overrides a central PFS miss in refractory upper gastrointestinal tumors, even as subgroup hazard ratios (2L OS HR 0.88 versus 3L+ OS HR 0.47) set up a critical Q2 2027 U.S. label-scope test.
Six Chinese-originated and global gastroesophageal ADCs compared
While Astellas Pharma’s (TSE: 4503) naked monoclonal antibody zolbetuximab (Vyloy) established CLDN18.2 in first-line HER2-negative gastric cancer (requiring ≥ 75% moderate-to-strong 2+/3+ membranous staining), ADCs have fractured the pretreated gastroesophageal market across three distinct axes: target biomarker cutoffs (all-comer TROP2 versus CLDN18.2 >= 25% at any intensity versus CLDN18.2 >= 75% at 2+/3+), cytotoxic payload classes (topoisomerase I inhibitors versus microtubule inhibitor MMAE), and commercial rights structures (full global out-licensing, ex-Greater China splits, or domestic pharma buyouts):
| Asset & Codes | Originator / Global Partner & Deal Structure | Target & Biomarker Cutoff | Linker & Payload (DAR) |
Pivotal Trial & Line (NCT ID) |
Primary Endpoint Readout (OS vs. PFS) |
Regulatory Status (as of Nov 21, 2026) |
|---|---|---|---|---|---|---|
sacituzumab tirumotecan (sac-TMT / MK-2870 / SKB264) |
Kelun-Biotech (06990.HK) / Merck (NYSE: MRK, ex-Greater China exclusive license) |
TROP2 (All-comer); central tissue testing for stratification, no cutoff exclusion |
Pyrimidine-sulfone hydrolyzable linker + belotecan-derivative Topo-I (KL610023, DAR ~7.4) |
TroFuse-015 (NCT06356311, n=473), global 3L+ GEA (4 mg/kg Days 1, 15, 29 Q6W vs. TPC) |
Primary OS: Met across all TROP2 subgroups; Secondary BICR-PFS: Missed; nominal ORR improvement |
Global regulatory filings planned (Nov 20, 2026); China 3L+ Phase 3 OptiTROP-Gastric01 (NCT06023797) ongoing |
sonesitatug vedotin (Sone-Ve / AZD0901 / CMG901) |
Keymed (02162.HK, 70% KYM) & Lepu (02157.HK, 30% KYM) / AstraZeneca (AZN, $63m upfront + $45m Ph3 milestone + up to $1.1b total, global incl. China) |
CLDN18.2 >= 25% of tumor cells at any intensity (~60% of GC/GEJ population) |
Protease-cleavable linker + MMAE microtubule payload (DAR ~4) |
CLARITY-Gastric01 (NCT06346392, n=594, 19 countries), global 2L+ GEC (2.2 mg/kg Q3W n=267 vs. ICT n=265) |
Co-primary 3L+ OS: Met (10.0 vs. 5.0 mo, HR 0.47, p<0.000001); Key secondary ITT OS: Met (10.6 vs. 6.4 mo, HR 0.58); Co-primary ITT BICR-PFS: Missed (4.2 vs. 3.8 mo, p=0.0532) |
U.S. FDA BLA Priority Review (Nov 19, 2026; PDUFA Q2 2027); China NMPA (CDE) NDA accepted (Oct 8, 2026); EU under review |
arcotatug tavatecan (IBI343 / TAK-921) |
Innovent Biologics (01801.HK) / Takeda (TSE: 4502 / NYSE: TAK, Oct 2025 $1.2b upfront / $11.4b package for ex-Greater China rights) |
CLDN18.2 >= 75% of tumor cells at 2+/3+ membranous intensity |
Cleavable linker + exatecan Topo-I payload (DAR ~4) with Fc-silenced antibody |
G-HOPE-001 (NCT06238843), multi-regional 3L+ GC/GEJ vs. investigator’s choice |
Co-primary PFS: Met at June 2026 interim analysis; co-primary OS maturing |
China NMPA NDA accepted under Priority Review (June 2026); global filings pending mature OS |
vetecotatug vedotin (LM-302 / TPX-4589) |
LaNova Medicines / Sino Biopharmaceutical (01177.HK, acquired via ~$500m net buyout of LaNova in July 2025) |
CLDN18.2 positive (>= 25% at 2+/3+ in 1L Phase 3 combination) |
Cleavable valine-citrulline linker + MMAE payload (DAR ~4) |
China Phase 3 (NCT05934331), 3L+ GC/GEJ; plus 1L Phase 3 + PD-1 (dosed Apr 2026) |
Interim dual endpoints: Met (June 2026 announcement; numerical effect sizes slated for early 2027 congress) | China NMPA NDA accepted under Priority Review (June 23, 2026); U.S. FDA Orphan Drug Designation |
SHR-A1904 |
Jiangsu Hengrui (600276.SS / 01276.HK) (wholly owned) |
CLDN18.2 positive (Phase 1 Nature Medicine Sept 2025) |
Cleavable linker + proprietary Topo-I payload |
China Phase 3 (NCT06649292, estimated n=524), 2L GC/GEJ vs. paclitaxel/docetaxel/irinotecan |
Single primary endpoint: OS (recruiting; primary completion target Sept 20, 2027) |
China CDE Breakthrough Therapy Designation (BTD, Dec 26, 2025) |
iza-bren (BL-B01D1 / izalontamab brengitecan) |
Sichuan Biokin / SystImmune (688506.SS) / BMS (NYSE: BMY, $800m upfront + $500m milestones paid) |
EGFR×HER3 bispecific (broad epithelial expression in HER2-negative GC/GEJ) |
Cleavable linker + Ed-04 camptothecin Topo-I payload (DAR ~8) |
China Phase 3 (NCT06496516, 2L+ GC/GEJ) & Phase 2 1L HER2- GC/GEJ + sintilimab |
Phase 2 1L HER2- GC/GEJ + sintilimab poster at ESMO Asia (Dec 4, 2026, 17:15 SGT, Prof. He Wei) |
Phase 3 recruiting in 2L+ GC/GEJ; approved/filed in NSCLC and NPC |
Why both Phase 3 trials hit OS while missing central PFS
In solid-tumor oncology, drugs far more commonly achieve progression-free survival (PFS) while failing to demonstrate overall survival (OS) after post-progression crossover. Seeing two independent global Phase 3 trials—one with a TROP2 Topo-I ADC (TroFuse-015) and one with a CLDN18.2 MMAE ADC (CLARITY-Gastric01)—deliver the exact opposite outcome (OS positive, BICR-PFS negative) points to three structural features of heavily pretreated gastroesophageal carcinoma:
- Rapid first-scan progression compresses median
PFSseparation: In3L+gastric andGEJadenocarcinoma, standard single-agent chemotherapy comparators (trifluridine/tipiracil[Lonsurf],irinotecan,paclitaxel,docetaxel, or China-specificapatinib) typically progress at or near the first scheduled radiographic assessment at Week 6 to Week 12. InCLARITY-Gastric01, medianBICR-PFSin theITTpopulation was 4.2 months (95% CI, 3.5–5.3) onsonesitatug vedotinversus 3.8 months (95% CI, 3.0–4.2) on comparator therapy (HR 0.77, p=0.053193). When nearly half of patients progress around the second restaging scan, the medianPFSpoint estimate barely moves, whereas the hazard ratio and survival tail capture durable responders—driving a doubling of 12-monthOSin3L+patients from 18.1% to 38.1% (median OS 10.0 vs. 5.0 months, HR 0.47). - High central-versus-local radiographic discordance in peritoneal and gastric wall disease: Advanced gastric cancer frequently metastasizes to the peritoneum, omentum, and retroperitoneal lymph nodes, accompanied by non-measurable malignant ascites and diffuse primary gastric wall thickening. Blinded central radiologists (
BICR) reading scans without clinical context frequently call early equivocal fluid changes or non-target lesion shifts differently from treating physicians. InCLARITY-Gastric01, whileITTBICR-PFSmissed statistical significance (4.2 vs. 3.8 months, HR 0.77), investigator-assessedPFSin the exact sameITTpopulation showed a clear 4.4 versus 3.0 month separation (HR 0.59,95% CI, 0.48–0.73), and3L+BICR-PFSseparated at 4.1 versus 2.7 months (HR 0.56,95% CI, 0.43–0.74, though not formally tested under the multiplicity hierarchy). - Different trial endpoint hierarchies determined headline success: Merck designed
TroFuse-015(n=473) exclusively in3L+GEAwithOSas the sole primary endpoint andBICR-PFSrelegated to a secondary endpoint—insulatingsac-TMTfrom central radiographic noise. Similarly, Jiangsu Hengrui’s ongoing 524-patient Phase 3 trial ofSHR-A1904in2LCLDN18.2-positiveGC/GEJ(NCT06649292) usesOSas its single primary endpoint. By contrast, AstraZeneca designedCLARITY-Gastric01(n=594) across a combined2L+population with dual primary endpoints (3L+ OSandITT 2L+ BICR-PFS), winning the trial on the3L+ OSalpha split while missing theITT BICR-PFSgate.
The Q2 2027 FDA label question for sonesitatug vedotin: 2L+ or 3L+?
Although AstraZeneca’s BLA was accepted under Priority Review for the broad 2L+ CLDN18.2 >= 25% population, the subgroup forest plot presented by Professor Xu Ruihua at the 2026 ESMO Presidential Symposium highlights a sharp regulatory question for the FDA’s Oncology Center of Excellence (OCE) ahead of the Q2 2027 PDUFA date:
- Biomarker cutoff breadth is well-supported: Across expression strata in
CLARITY-Gastric01, patients with high expression (CLDN18.2 >= 75%) achieved a medianOSof 10.6 versus 6.4 months (HR 0.59,95% CI, 0.45–0.78), while those in the lower25% to <75%bracket achieved 10.5 versus 6.2 months (HR 0.63,95% CI, 0.42–0.94). That consistency validatessonesitatug vedotin’sMMAEbystander effect and supports its lower ≥ 25% threshold (covering ~60% of gastric tumors) over the stricter ≥ 75% at2+/3+cutoff used by Innovent and Takeda’sarcotatug tavatecan(IBI343) inG-HOPE-001. - Line-of-therapy and anatomic site heterogeneity is much wider: While
3L+patients (n=178 vs. 177, ~67% of the2.2 mg/kgcohort) delivered an overwhelmingOSbenefit (10.0 versus 5.0 months,HR 0.47), the unadjustedOShazard ratio among2Lpatients wasHR 0.88(95% CI, 0.60–1.30)—where active comparator regimens includedramucirumab + paclitaxel—andHR 1.08(95% CI, 0.68–1.71) in the gastroesophageal junction and esophageal adenocarcinoma (GEJ/EAC) subset.
For sac-TMT (MK-2870), Merck avoided the 2L ramucirumab + paclitaxel comparator hurdle in TroFuse-015 by restricting enrollment to 3L+ patients—and gained an all-comer survival readout that requires no companion diagnostic cutoff at all (OS benefit consistent regardless of TROP2 expression). For Kelun-Biotech (06990.HK), which completed its generational chairmanship transition to Liu Sichuan on November 18, TroFuse-015 represents the second positive global Phase 3 readout under Merck’s 18-trial global TroFuse program, expanding sac-TMT beyond lung, breast, and gynecologic malignancies into upper gastrointestinal oncology.
What to watch next
- December 4, 2026 (
ESMO Asia, Singapore): SystImmune and Sichuan Biokin (688506.SS) will present seven abstracts acrossiza-bren(BL-B01D1, including the1LHER2-negativeGC/GEJ+sintilimabPhase 2 poster at17:15 SGT) andHER2ADCT-Bren(BL-M07D1, oral presentations in colorectal and urothelial cancers on December 4 and 6). - Early 2027 gastrointestinal oncology congress (
ASCO GI): Expected full numerical presentation ofTroFuse-015(median OS, hazard ratio, Grade ≥ 3 stomatitis and hematologic toxicity rates, andTROP2-high vs.TROP2-low subgroup curves) alongside Sino Biopharm’s (01177.HK) Phase 3 readout forvetecotatug vedotin(LM-302). - Q2 2027 U.S. FDA
PDUFAdecision forsonesitatug vedotin(AZD0901): Whether the FDA grants AstraZeneca the full2L+CLDN18.2 >= 25%gastric/GEJ/EACindication or narrows the U.S. label to3L+gastric adenocarcinoma, and whether any approval milestone is triggered for Keymed (70%ofKYM) and Lepu Biopharma (30%ofKYM).